info@biomedres.us
+1 (502) 904-2126
One Westbrook Corporate Center, Suite 300, Westchester, IL 60154, USA
Site Map
 ISSN: 2574 -1241
Received: June 29, 2026; Published: July 13, 2026
*Corresponding author: Zhang Zhe, Department of Integrated Traditional Chinese and Western Medicine, Hebei Provincial Hospital of Traditional Chinese Medicine, No. 389 Zhongshan East Road, Chang’an District, Shijiazhuang, Hebei 050011, China
DOI: 10.26717/BJSTR.2026.66.010298
Objective: To investigate the role of the TLR4/NF-κB signaling pathway in progressive cerebral infarction.
Methods: A total of 50 patients with progressive cerebral infarction admitted to our hospital were enrolled as
the observation group, along with 50 healthy individuals serving as the control group. The mRNA and protein
expression levels of NF- κB p65, the phosphorylation level of NF- κB p65 in peripheral blood mononuclear cells
(PBMCs), and the serum levels of tumor necrosis factor-α (TNF-α) and interleukin-1β (IL-1β) were measured in
both groups before and after treatment.
Results: After treatment, the mRNA and protein expression levels of NF- κB p65, as well as its phosphorylation
level in PBMCs, were significantly lower in the observation group than in the control group (P < 0.05). Similarly,
serum levels of TNF-α and IL-1βwere significantly reduced compared with those in the control group (P < 0.05).
Conclusion: Activation of the TLR4/NF- κB signaling pathway plays a critical role in the pathogenesis of progressive
cerebral infarction.
Abbreviations: PBMCs: Peripheral Blood Mononuclear Cells; TNF-α: Tumor Necrosis Factor-α; IL-1β: Interleukin-1β; PBS: Phosphate-Buffered Saline; HRP: Horseradish Peroxidase; ECL: Enhanced Chemiluminescence; BMI: Body Mass Index; LPS: Lipopolysaccharide
Progressive cerebral infarction is a subtype of ischemic stroke characterized by a higher rate of disability and mortality compared with other forms, drawing significant attention in the medical community. Clinically, it is generally defined as a stroke in which neurological function continues to deteriorate within 72 hours of onset despite treatment, with an increase of ≥2 points in the NIHSS score relative to baseline [1]. Oxidative stress and inflammation are currently recognized as key contributors to its pathogenesis [1].
The NF-κB signaling pathway is thought to play a central role in the development of progressive cerebral infarction [1]. Previous studies have demonstrated that TLR4 can activate NF-κB, promoting its nuclear translocation and initiating the expression of pro-inflammatory genes such as tumor necrosis factor-α (TNF-α) and interleukin- 1β (IL-1β) [2]. However, the specific role of the TLR4/NF-κB pathway in peripheral blood mononuclear cells (PBMCs) of patients with progressive cerebral infarction remains unclear. Therefore, this study aimed to investigate the activation status of the TLR4/NF- κB signaling pathway in PBMCs and the serum expression levels of related inflammatory factors, providing a theoretical basis for the clinical prevention and treatment of this condition.
Study Subjects
A total of 100 subjects were enrolled in this study, comprising 50 patients with progressive cerebral infarction in the experimental group and 50 healthy volunteers undergoing routine physical examinations during the same period as the control group. There were no significant differences between the two groups in terms of age, gender, or other baseline characteristics (P > 0.05), indicating that the groups were comparable.
Inclusion Criteria for the Experimental Group:
1. Diagnosis consistent with the Guidelines for the Diagnosis
and Treatment of Acute Ischemic Stroke in China (2018), with
first onset confirmed by cranial CT or MRI.
2. Acute onset with an admission NIHSS score > 0.
3. Neurological deterioration after admission, defined as an increase
of ≥2 points in the NIHSS score within 72 hours compared
with baseline, with no intracranial hemorrhage on repeat imaging.
4. Onset within 7 days at enrollment; age 18-80 years; no history
of hemorrhagic stroke or other major terminal illnesses.
5. Normal consciousness and stable vital signs.
6. Complete clinical data, hospitalization for more than 7 days,
and good compliance with treatment, examinations, and evaluations.
7. Normal liver and kidney function, electrocardiogram, blood
and urine routine, and coagulation tests on admission.
8. Provision of informed consent with a signed consent form.
Inclusion Criteria for the Control Group: Undergoing routine physical examinations at our hospital during the same period. No abnormalities on clinical, imaging, or laboratory evaluations. No history of acute or chronic inflammatory diseases or autoimmune disorders. Age- and gender-matched with the experimental group.
Exclusion Criteria: Children or elderly patients outside the study’s age range. Patients with severe organic diseases affecting the heart, liver, kidneys, or other major organs. Pregnant or lactating women. Individuals with known allergies to reagents used in this study. Patients with poor compliance or inability to cooperate with study procedures.
Detection of TLR4 mRNA Expression in PBMCs by RT-qPCR
Isolation of PBMCs: Five milliliters of fasting venous blood were collected in the early morning from each subject using heparin as an anticoagulant. PBMCs were isolated by density gradient centrifugation. Briefly, the anticoagulated blood was diluted 1:1 with phosphate- buffered saline (PBS) and carefully layered over Ficoll density gradient medium. The samples were then centrifuged at 2000 rpm for 20 minutes. The PBMCs from the intermediate buffy coat layer were collected, washed twice with PBS, and resuspended at a density of 1 × 10⁶ cells/mL for subsequent use.
Total RNA Extraction and cDNA Synthesis: Total RNA was extracted from 1 × 10⁶ PBMCs using the TRIzol reagent according to the manufacturer’s instructions. The concentration and purity of the RNA were assessed prior to use. One microgram of total RNA was reverse- transcribed into cDNA using the RevertAid First Strand cDNA Synthesis Kit, following the manufacturer’s protocol. The reaction conditions were 42°C for 60 minutes and 70°C for 5 minutes. The resulting cDNA was stored at −20°C until further analysis.
Real-Time Fluorescence Quantitative PCR (qPCR): The expression level of TLR4 mRNA was quantified using the SYBR Green method, with GAPDH serving as the internal reference. The primer sequences were as follows:
• TLR4 forward primer: 5’-AGGTTGCCAGGTGATTGTTG-3’
• TLR4 reverse primer: 5’-CAGTGCAGCCTCAACTTCAC-3’
• GAPDH forward primer: 5’-AGAAGGCTGGGGCTCATTTG-3’
• GAPDH reverse primer: 5’-AGGGGCCATCCACAGTCTTC-3’
qPCR reaction system and amplification conditions: The qPCR reaction was performed in a total volume of 25 μL, consisting of 2 μL cDNA, 0.8 μL each of forward and reverse primers, 12.5 μL of 2× UltraSYBR Mixture, and nuclease-free water to reach the final volume. The amplification procedure was as follows: pre-denaturation at 95°C for 10 minutes, followed by 40 cycles of 95°C for 15 seconds and 60°C for 1 minute. A melting curve analysis was subsequently performed from 65°C to 95°C to confirm the specificity of the amplified products. The relative expression level of TLR4 mRNA was calculated using the 2⁻ΔΔCt method. The calculations were performed as follows: ΔCt (target gene) = Ct (target gene) − Ct (internal reference gene) ΔΔCt = ΔCt (experimental group) − ΔCt (control group) Relative expression level = 2⁻ΔΔCt Using the above detection method, the expression level of TLR4 mRNA can be accurately and specifically quantified, providing a reliable basis for subsequent analysis of the activation status of the TLR4 signaling pathway. RT-qPCR is simple, rapid, and highly reproducible, and is widely regarded as the “gold standard” for quantitative gene expression analysis.
Detection of Tlr4 Protein Expression and NF-ΚB P65 Phosphorylation in PBMCs by Western Blot
Protein Extraction: An appropriate number of PBMCs were lysed on ice for 30 minutes using RIPA lysis buffer. The lysate was then centrifuged at 12,000 rpm and 4°C for 15 minutes, and the supernatant was collected. Protein concentration was determined using the BCA method, adjusted to 2 μg/μL, and the samples were stored at −80°C until further use.
SDS-Page Electrophoresis and Membrane Transfer: 40 micrograms of protein sample were mixed with loading buffer and denatured by boiling at 100°C for 5 minutes. Proteins were separated on a 10% SDS-PAGE gel and subsequently transferred to a PVDF membrane using the semi-dry transfer method.
Primary Antibody Incubation: The PVDF membrane was blocked with 5% skimmed milk for 2 hours at room temperature, then incubated overnight at 4°C with primary antibodies against TLR4 (1:500), NF-κB p65 (1:1000), and phosphorylated p65 (p-p65, 1:1000).
Secondary Antibody Incubation: After three washes with TBST for 5 minutes each, the membrane was incubated with horseradish peroxidase (HRP)-conjugated goat anti-rabbit or goat anti-mouse secondary antibody (1:5000) at room temperature for 1 hour.
ECL Development: After thorough washing, the PVDF membrane was incubated with enhanced chemiluminescence (ECL) reagent, and protein bands were visualized using a ChemiDoc XRS+ gel imaging system. β-Actin was used as an internal reference, and the relative expression levels of target proteins were quantified using Image Lab software. Western blotting allows for specific and semi-quantitative detection of target protein expression. By analyzing the levels of TLR4, NF-κB p65, and p-p65, the activation status of the TLR4/NF-κB signaling pathway can be assessed. Additionally, Western blotting is highly sensitive and provides clear, visual results, making it an essential tool for investigating protein expression and function.
Detection of Serum TNF-α and IL-1β Levels by ELISA
Serum Sample Collection: 3 milliliters of fasting venous blood were collected from each subject in the early morning. The samples were allowed to clot at room temperature for 30 minutes and then centrifuged at 3,000 rpm for 10 minutes to separate the serum. The serum was aliquoted and stored at −80°C until further analysis.
ELISA Detection: Serum samples and all reagents were equilibrated to room temperature prior to use. Blank wells, standard wells, and test wells were prepared. Standard wells were loaded with standard solutions, test wells with appropriately diluted serum samples, and blank wells were left empty. HRP-conjugated detection antibody was added to all wells except the blank wells, followed by incubation at 37°C for 30 minutes. The liquid in the wells was discarded, and the wells were washed five times with wash buffer. Substrates A and B were then added sequentially, followed by color development at 37°C in the dark for 10-20 minutes. Stop solution was added to terminate the reaction, and absorbance (OD value) was measured at 450 nm. A standard curve was constructed from the OD values of the standards, and the concentrations of TNF-α and IL-1β in the test samples were calculated accordingly.
ELISA is simple to perform, highly specific, and sensitive, enabling accurate quantification of cytokine levels in serum. Measurement of inflammatory mediators such as TNF-α and IL-1β reflects the systemic inflammatory state and disease severity, providing a valuable basis for the diagnosis and assessment of progressive cerebral infarction.
Statistical analyses were performed using SPSS version 23.0. Measurement data conforming to a normal distribution were expressed as mean ± standard deviation (x̄ ± s), and comparisons between groups were conducted using the independent-samples t-test. Categorical data were presented as counts and percentages [n (%)], and group comparisons were performed using the chi-square test. A P value < 0.05 was considered statistically significant.
General Data
There were no statistically significant differences between the two groups in baseline characteristics, including gender, age, height, weight, body mass index (BMI), heart rate, systolic blood pressure, and diastolic blood pressure (P > 0.05), indicating that the groups were well matched. Detailed results are presented in Table 1. As shown in Table 1, there were no significant differences between the experimental and control groups in terms of gender distribution, age, physical measurements, vital signs, or other baseline characteristics. The comparability of these data ensures the reliability of subsequent statistical analyses. The onset of progressive cerebral infarction is influenced by multiple factors, including viral infection, autoimmune disorders, diabetes mellitus, and psychological stress. Selecting study subjects with matched baseline characteristics helps minimize the influence of confounding factors, ensuring comparable demographic and physiological profiles between groups. This approach allows for a more accurate assessment of the impact of TLR4/NF-κB signaling pathway activation on the development and progression of progressive cerebral infarction.
Table 1: Comparison of general information in two groups (x±s).
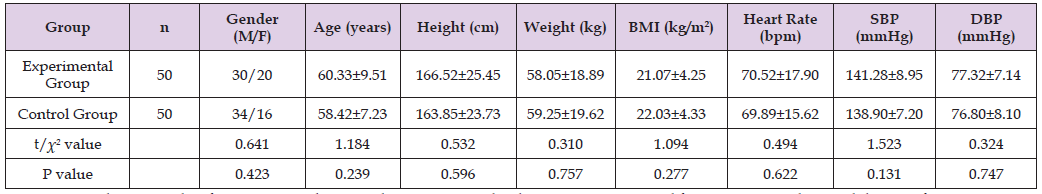
Note: BMI: Body Mass Index; for comparison between the two groups, the chi square test was used for enumeration data, and the t test for measurement data.
Expression of TLR4 mRNA and Protein in PBMCs
RT-qPCR and Western blot analyses demonstrated that both TLR4 mRNA and protein expression levels in PBMCs were significantly higher in the experimental group compared with the control group (P < 0.05). These findings indicate that the TLR4 signaling pathway is abnormally activated in patients with progressive cerebral infarction.
Phosphorylation Level of NF κB p65 in PBMCs
Western blot analysis revealed that the phosphorylation level
of NF-κB p65 in PBMCs was significantly higher in the experimental group compared with the control group (P < 0.05), indicating excessive activation of the NF-κB signaling pathway in patients with progressive cerebral infarction. This study demonstrated significantly increased phosphorylation levels of the NF-κB p65 subunit in PBMCs from patients with progressive cerebral infarction, indicating enhanced endogenous inflammatory responses. These findings suggest that sustained activation of the NF-κB signaling pathway may contribute to disease progression.
Comparison of Serum TNF α and IL 1β Levels
ELISA results demonstrated that serum levels of TNF-α and IL- 1β in the experimental group were 149.50 ± 12.12 ng/L and 255.50 ± 19.19 ng/L, respectively, which were significantly higher than the levels observed in the control group (102.10 ± 10.60 ng/L and 105.20 ± 12.80 ng/L; P < 0.05). These findings indicate that patients with progressive cerebral infarction exhibit markedly elevated systemic inflammatory responses.
As a key member of the Toll-like receptor family, TLR4 serves as an important pattern recognition receptor linking innate immunity and inflammation. It recognizes exogenous pathogen-associated molecular patterns, such as bacterial lipopolysaccharide (LPS), and can also be activated by endogenous danger signals, including heat shock proteins and hyaluronic acid, released following neuronal injury. Thus, TLR4 plays a central role in both infectious and sterile inflammatory responses [2-4]. Excessive activation of the TLR4/NF-κB signaling pathway can directly disrupt the inflammatory microenvironment. In this study, serum levels of pro-inflammatory factors such as TNF-α and IL-1β were significantly [5-9] elevated in patients. These mediators may exacerbate neuronal injury through multiple mechanisms:
1. Exerting direct cytotoxic effects on neurons, leading to apoptosis or necrosis;
2. Activating astrocytes and microglia, thereby amplifying local inflammation; and
3. Impairing the blood-nerve barrier [10-15], facilitating immune cell infiltration. This inflammatory vicious cycle, driven by TLR4/NF-κB signaling and mediated by TNF-α and IL-1β, ultimately contributes to neurological dysfunction and the progressive deterioration of symptoms in patients [16-18].
In summary, aberrant activation of the TLR4/NF-κB signaling pathway, along with overexpression of its downstream inflammatory mediators TNF-α and IL-1β, plays a central role in the development and progression of progressive cerebral infarction. The findings of this study not only enhance the understanding of the disease’s pathophysiological mechanisms but also provide a theoretical basis and potential targets for the development of precise therapeutic strategies aimed at pathway inhibition.
This study was supported by the Health Commission of Hebei Province (Grant No. 20250857).
Government-funded Excellent Clinical Talent Training Program (Grant No.: ZF2026268).
This research was supported by the
Hebei Provincial Health Commission Project (Grant No. 20250857)
Government-funded Excellent Clinical Talent Training Program (Grant No. ZF2026268)
The datasets used and/or analyzed during the current study are available from the corresponding author on reasonable request.
This clinical study was approved by the Ethics Committee of Hebei Provincial Hospital of Traditional Chinese Medicine (Approval No.: HBZY2026-KY-011-01, Date: January 22, 2026). All procedures were performed in accordance with the ethical principles of the Declaration of Helsinki and relevant national guidelines. Written informed consent was obtained from all participants prior to enrollment.
Not applicable.
The authors declare that they have no competing interests.
All patients participating in this study have provided written informed consent for the publication of their relevant clinical data and research results. All personal identifiable information of the participants has been fully anonymized and de-identified to protect patient privacy. No sensitive personal information, including name, ID number, address and other identifiable details, is disclosed in this article. All participants agreed that the anonymized clinical data and experimental data generated in this study can be used for academic research, journal publication and related academic exchanges without any restriction.
Zhang Zhe conceived, designed and did statistical analysis & editing of manuscript, is responsible for integrity of research.
Jiang Xiaohong, Jin Xiaofei did data collection and manuscript writing. Jin Xiaofei did review and final approval of manuscript. Both authors have confirmed and verified the authenticity of the raw data.

International Association of Landscape Archaeology, Czech Glass Society, Czech Republic

Department of Chemistry, Semenov Institute of Chemical Physics, USSR Academy of Sciences, Moscow, Russia

Neurology, LA BioMed Research Institute, USA

Associate Professor at Department of Breast and Thyorid Surgey, Chongqing General Hospital, China

Clinical Radiologist (MD) - Department of RADIOLOGY, Cosenza Hospital, Cosenza, Italy





 Abstract
 PDF




























